
Placement of an artificial urinary sphincter
The solution for severe male incontinence
Discover the artificial urinary sphincter, the gold standard treatment for severe urinary incontinence in men, with Professor François Haab.
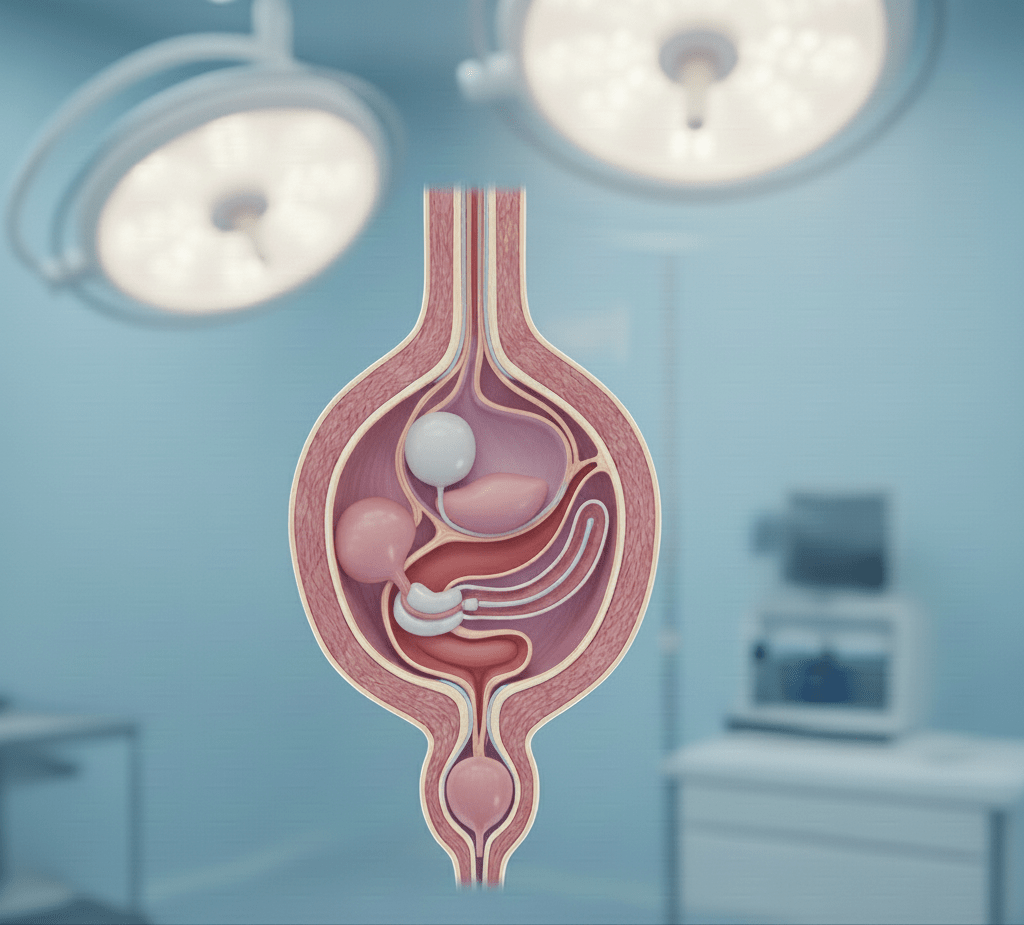
What does this gesture consist of?
An artificial urinary sphincter (AUS) is an implantable device that replaces or supplements the function of the natural sphincter when it is impaired. It consists of three main parts: an inflatable cuff surrounding the urethra, a control pump (manual pump), and a reservoir balloon. When activated, the device compresses the urethra to prevent urinary leakage. To urinate, the patient activates the pump, which opens the urethra for the necessary time, and then the system closes automatically. This procedure is particularly indicated in cases of post-prostatectomy incontinence (urinary incontinence after prostate surgery), when stress urinary leakage is severe and persists despite well-conducted rehabilitation. It is considered the standard treatment in this situation.

In what cases?
Indications
When the implantation of an artificial urinary sphincter is proposed:
- Severe to major urinary incontinence after prostate surgery (radical prostatectomy), or after prostate interventions, if pelvic floor rehabilitation is not sufficient.
- Significant stress urinary incontinence, or heavy leakage (often > 300-500 mL/24h) depending on the case.
- Patient’s ability to manipulate the manual control pump (skill, dexterity, understanding) to trigger urination.
- Sterile urine, no urinary tract infection at the time of the procedure.
- Favorable skin condition, good healing expected, no major history that contraindicates the procedure (e.g., chronic infection, healing problems).
Operating technique & procedure
Here is how the implantation of an artificial sphincter typically proceeds: 1. Preparation before the operation
- Clinical assessment: urodynamics, flowmetry, post-void residual assessment, urethral examination (endoscopy) to rule out any obstruction.
- Urine analysis to ensure the absence of infection.
- Information and consent, explanation of the device, the procedures, the post-operative care.
2. Surgical intervention
- Anesthesia: general or regional depending on the patient.
- Incisions: often one in the perineum, one in the inguinal fold or in the abdominal region depending on the type of sphincter used. Sometimes via the scrotal route in men in certain cases.
- The cuff is placed around the urethra, and the reservoir balloon and pump are positioned. The components are connected, and the system is closed.
- The sphincter is left deactivated during the healing period (often several weeks) before being put into service.
3. Hospitalization and follow-up
Presentation and background


Expected results & effectiveness
- The rate of complete continence (no leakage) or social continence (very minimal leakage acceptable) is high: many series report perfect continence in ~ 75% of cases, with significant improvement in most of the others.
- Patient satisfaction is very good, especially after other solutions have failed (rehabilitation, slings, etc.).
- Device lifespan: although mechanical, the components may require overhauls or replacements over the years (pump, sleeve, leak, wear).
Why choose this technique? Its advantages
Expertise
Artificial urinary sphincter: how to use it on a daily basis?

Limitations/Risks, Contraindications & Precautions
Limitations / risks:
- Risk of infection (prosthesis, pumps), sometimes requiring explantation.
- Risk of urethral erosion or urethral atrophy in the long term.
- Mechanical complications or wear and tear of the device (pump, tank, leaks).
- Need to operate the pump manually: requires physical/motor skills.
- Cost of the intervention and follow-up.
Contraindications & precautions
- Untreated active urinary tract infection.
- Poor condition of the skin or tissues at the implant site (wounds, significant radiotherapy, poor vascularization).
- Patient unable to understand or operate the device (pump).
- Severe, uncorrected lower urinary tract disorders (e.g., untreated urethral stricture) or persistent obstruction.
Specialist in urological surgery
Experience
Urinary incontinence: artificial sphincter surgery (uncensored) – Professor François Haab

My journey in video
I made this video to introduce myself and describe my background and expertise.
Make an appointment
I welcome you to my office in Paris to discuss your expectations and offer you the most suitable solution: medical penoplasty or surgical penoplasty.
FAQ – Frequently Asked Questions
How does an artificial urinary sphincter work?
The device consists of an inflatable cuff placed around the urethra, a pump housed in the scrotum, and a pressure-regulating balloon. The cuff continuously compresses the urethra; to urinate, the pump is simply activated, which deflates it for a few minutes.
Who is the artificial sphincter intended for?
This is the standard treatment for severe urinary incontinence in men, particularly after prostatectomy, when other treatments have failed or are insufficient. It may also be offered for certain complex cases of female incontinence.
How is it used on a daily basis?
Its use quickly becomes second nature: a simple press on the pump, through the skin of the scrotum, allows for normal urination. The device is activated approximately 6 weeks after insertion, once the healing process is complete.
What is the lifespan of the device?
The artificial sphincter typically functions for 10 to 15 years. In case of wear or malfunction, all or part of the device can be replaced during a subsequent procedure.
Pr François Haab's expertise
Chirurgien Urologue à Paris

Placement of an artificial urinary sphincter: there are solutions.