
Urinary incontinence surgery
Regaining urinary control and quality of life
Discover the urinary incontinence surgery options offered by Professor François Haab: minimally invasive techniques, lasting results and personalized care to regain optimal continence.
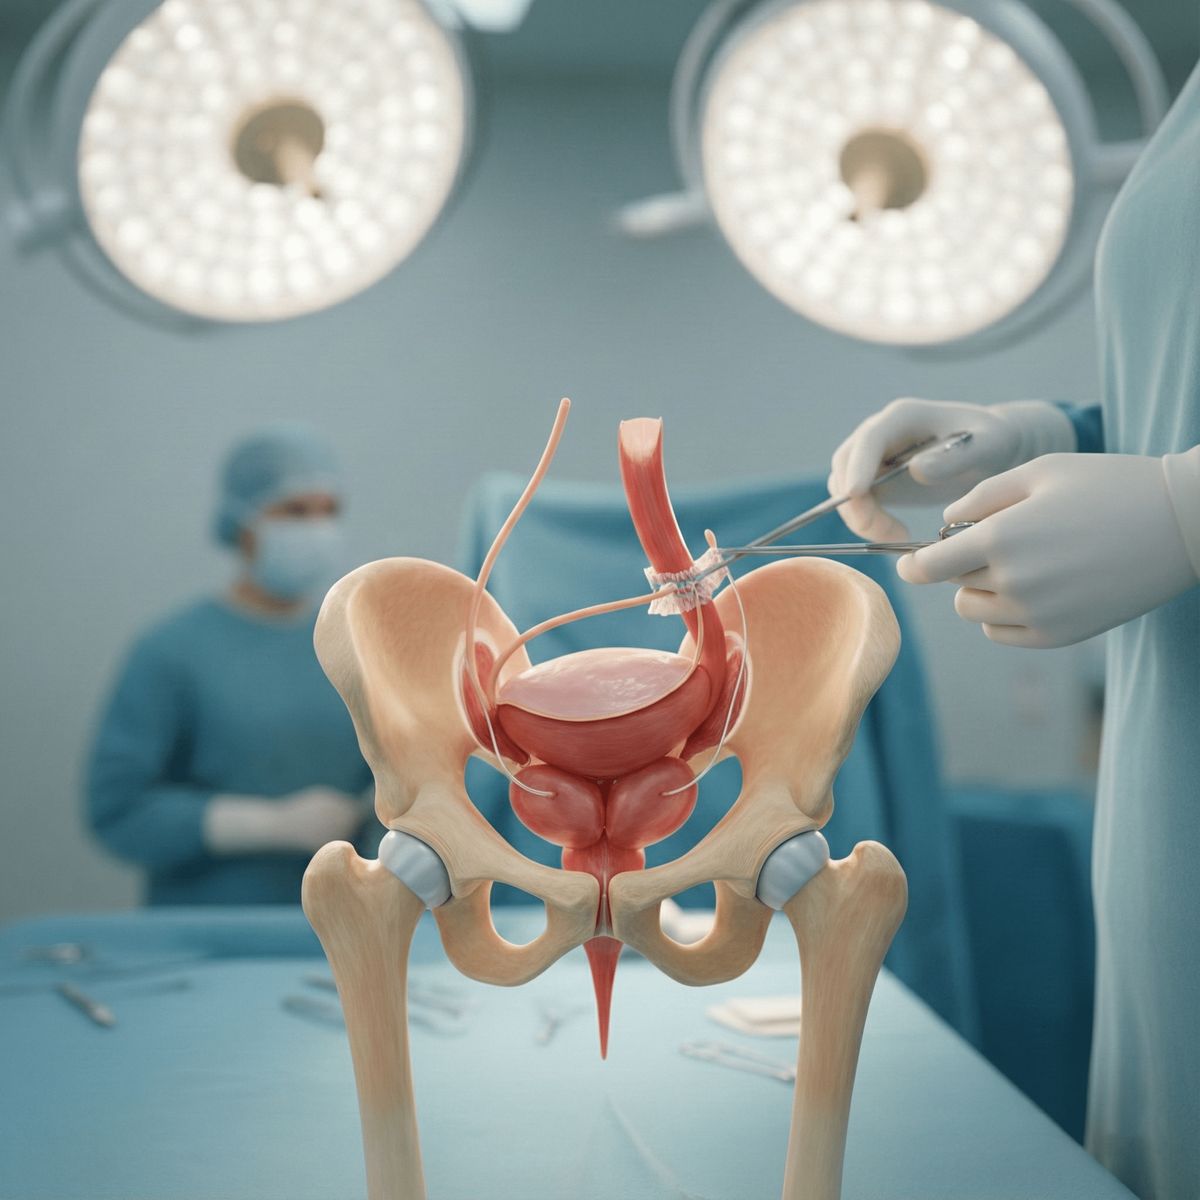
What is urinary incontinence?
Urinary incontinence is the involuntary loss of urine. It can be triggered by physical exertion (coughing, sports, etc.), a sudden and uncontrollable urge to urinate, or a malfunction of the sphincter. It can significantly impact quality of life: social embarrassment, limitations in activities, and intimate discomfort. When medical treatments or rehabilitation are insufficient, surgery can offer lasting relief .

The different types of incontinence
1. Stress urinary incontinence (SUI )
- Urine loss during exertion: coughing, laughing, brisk walking, carrying heavy loads.
- Often linked to a lack of urethral support or weakness of the pelvic tissues.
2. Urge incontinence (UIU)
- Urgent urges that cannot be postponed.
- Associated with overactive bladder or involuntary detrusor contractions.
3. Mixed incontinence
- Association of effort + urgency.
4. Incontinence due to sphincter insufficiency
- Continuous or near-continuous leakage linked to a weak sphincter (prostatectomy, previous surgery…).
Expertise in urinary incontinence in men
 Expertise Incontinence urinaire chez l'hommePr François Haab
When should surgery be recommended?
Surgery is considered when:
Penetical rehabilitation has not provided sufficient improvement.
Medications are ineffective or poorly tolerated.
Urinary incontinence significantly impacts daily life.
Urological assessment (clinical examination + urodynamics) confirms an anatomical or functional cause that may benefit from surgical intervention.
The main surgical options
Depending on the cause of the incontinence, several techniques can be offered : 1. Suburethral sling (TVT/TOT) — female
- It supports the urethra like a “hammock”.
- Indicated for female stress incontinence.
- Minimally invasive technique, fast results.
2. Periurethral balloons
- Implantation of two balloons around the urethra to increase resistance.
- Adjustable upon consultation.
- An interesting solution in cases of moderate SUI or strip failure.
3. Artificial urinary sphincter (AUS) — primarily in men
- Standard treatment for severe sphincter insufficiency.
- A cuff surrounds the urethra and deflates during urination.
- Very good results after prostatectomy.
4. Periurethral injections
- Filling around the urethra to improve coaptation.
- A minimally invasive solution, but the effect is sometimes temporary.
5. Prolapse and incontinence surgeries
- Some cases of pelvic organ prolapse cause or worsen incontinence.
- Surgical correction of prolapse and possible placement of a sling.
Procedure of the intervention
1. Before surgery
- Urodynamic assessment
- ECBU (infection screening)
- Anesthesia consultation
- Discussion of the choice of technique according to the patient’s profile
2. The day of the operation
- The procedure is often minimally invasive and quick (20 to 60 min).
- Performed under local, spinal or general anesthesia.
3. After the procedure
- Return home the same day or the next day.
- Rapid resumption of daily activities according to the procedure.
- Remote monitoring to assess effectiveness.
Expertise in urinary incontinence in women
 Expertise Incontinence urinaire chez la femmePr François Haab
Advantages of surgery
Risks and limitations
Like any intervention, there are limits:
- Post-operative infection or hematoma
- Urinary retention (rare) depending on the blood pressure or device
- Transient pain (groin, perineum, surgical area)
- Risk of failure or partial improvement depending on the technique
- Specific risks: erosion (strip), mechanical dysfunction (AUS)
The precise choice of technique strongly influences the result: hence the importance of an expert evaluation.
Expertise
Incontinence surgery: Is it normal to experience pain after the operation? | Dr. Haab
 Chirurgie de l’incontinence : est-il normal d’avoir des douleurs après l'opération ? | Pr HaabPr François Haab
Specialist in urinary incontinence
My review in video
Discover my explanatory videos on incontinence in women and men.
FAQ – Frequently Asked Questions
When should incontinence surgery be considered?
Surgery is recommended when incontinence persists despite well-conducted pelvic floor rehabilitation and impacts quality of life. It primarily addresses stress incontinence, following a comprehensive assessment to determine the underlying mechanism.
What surgical techniques are available?
The main options are transurethral sling placement (TOT/TVT) in women, periurethral bulking agents, and artificial urinary sphincter devices for severe incontinence, particularly in men. The choice depends on the type of incontinence and your medical history.
Is it normal to have pain after the operation?
Moderate and temporary pain is common in the days following the procedure and is relieved with simple painkillers. Persistent or severe pain is not normal and should prompt a follow-up consultation.
What results can be expected from surgery?
Success rates for suburethral slings exceed 85% at 5 years for stress incontinence. The artificial sphincter provides social continence to more than 90% of patients. Results depend on a well-defined indication, hence the importance of preoperative assessment.
Pr François Haab's expertise
Chirurgien Urologue à Paris

Urinary incontinence surgery: there are solutions.